Why One Side Is Always Tighter and Whether You Should Chase Symmetry
Quick Answer: Asymmetry is the norm, not the exception - organ placement, dominant-hand use, leg length differences of up to about 1cm, and rib cage rotation are all common and largely benign. Chase symmetry only when the difference is large, worsening, painful, or limiting a specific task. Otherwise train both sides, start each set with the restricted side, and match the reps - which addresses functional asymmetry without pursuing a structural symmetry you were never going to have.
Most asymmetry needs managing, not correcting.


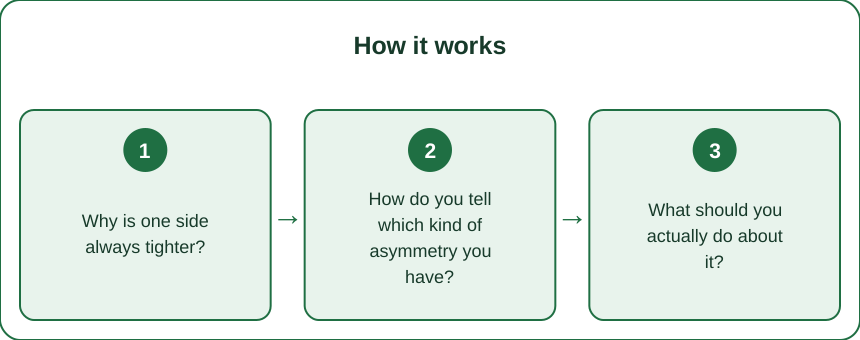
Why is one side always tighter?
Several reasons stack, and most of them are not fixable by stretching.
Structural asymmetry is built in. Your liver sits on the right and is heavy. Your heart sits left. Your diaphragm has a larger, more mechanically advantaged right dome. The result is a subtle default rotation and rib position that is present in essentially everyone, and it produces a consistent pattern - the right hip and left shoulder tend to be more restricted in more people than chance would predict. This is anatomy, not a training error.
Leg length differences are common. Differences up to around 1cm are found in a large share of the population and are generally considered clinically unimportant. They still change pelvic position slightly, which changes how each hip loads and what each side feels like at end range.
Handedness organizes everything. Decades of reaching, carrying, kicking, and turning with a preference produces genuine differences in muscle mass, tendon stiffness, and motor control between sides. This is adaptation, not dysfunction, and it is the same process that makes a tennis player’s serving arm bone denser.
Habit position matters more than people think. Always sitting with the same leg crossed, always carrying a bag on one shoulder, always sleeping on one side, always standing with weight on one hip. Eight hours a day of an asymmetric position beats ten minutes of stretching, every time.
Joint structure varies side to side. Hip socket depth and femoral neck angle can differ between your own two hips. When the restriction is bony, stretching cannot change it - the bones are meeting, and more force just irritates the joint. This is the single most important distinction in the whole topic, and it is why some asymmetries never budge no matter how consistently they are stretched.
How do you tell which kind of asymmetry you have?
Three tests that separate the categories.
Test 1: does it change with warm-up? Compare both sides cold, then again after ten minutes of general movement. A difference that shrinks substantially when warm is soft tissue and motor control - that responds to training. A difference that is identical warm and cold is more likely structural.
Test 2: what does end range feel like? This is the most informative and the most overlooked.
- A stretch sensation - pulling, lengthening, tolerable - suggests soft tissue and responds to mobility work
- A hard, abrupt block, often with pinching at the front of the joint suggests bone meeting bone. Stop. Pushing here produces irritation, not range.
- Sharp, electrical, or radiating sensation suggests nerve tension, which needs a different approach entirely and possibly assessment
Test 3: active versus passive range. Move the limb yourself, then have gravity or a hand move it further. If passive range is much greater than active, the restriction is control rather than tissue length - you have the range and cannot access it. That is a strength and motor control problem, and stretching will not fix it. This is the single most common misdiagnosis in mobility work.
When to get it assessed rather than self-manage:
- Pain, not just tightness
- A difference that is worsening over months
- Sudden onset asymmetry after an injury
- Numbness, tingling, or radiating symptoms
- Visible difference in leg length or in how you walk
This is general information, not medical advice. Persistent one-sided restriction with pain deserves a proper assessment rather than more stretching.

What should you actually do about it?
Manage the functional part, accept the structural part, and change the habit part.
Train unilaterally and lead with the restricted side. Do the harder side first, note the reps, and match the easier side to it rather than the reverse. Doing the strong side first sets a target the weak side cannot meet and widens the gap over months. Leading with the restricted side is the single most effective structural change to a program, and it costs nothing.
Add range, do not just stretch into it. End-range strength is what makes mobility stick. Passive stretching produces range you cannot control, which the nervous system tends to give back within days. Loaded end-range work - a controlled pause at the deepest position of a split squat, or a weighted end-range hold - produces changes that persist.
Audit the eight hours, not the ten minutes. Which side do you cross? Which shoulder carries the bag? Which side do you sleep on? Which foot do you stand on while waiting? Alternating a few of these does more for a habitual asymmetry than any stretching routine, because the exposure is a hundred times greater.
Give it 8 to 12 weeks before judging. Mobility changes are slow, and asymmetry work is slower because you are working against an entrenched pattern.
Then decide whether it matters. If the difference is small, painless, and not limiting anything you do, the correct action is often to stop working on it. Time spent chasing a 5 degree hip rotation difference is time not spent on strength or conditioning, and the evidence linking small asymmetries to injury risk is much weaker than the internet suggests.
Where it does matter: large differences, over roughly 15 to 20 percent in strength or a clear visible difference in range; anything painful; anything that is worsening; and asymmetries that directly limit a task you care about, such as one hip that will not allow a full squat.
Myth vs Fact: Asymmetry and Injury
Myth: Asymmetry causes injury. Fact: The research linking small asymmetries to injury is inconsistent. Large differences - roughly 15 percent or more in strength - show some association. Small ones are essentially universal and poorly predictive.
Myth: Everyone should aim for perfect symmetry. Fact: Nobody has it. Athletes in asymmetric sports have pronounced differences and perform at the highest level. Function matters; matching numbers do not.
Myth: If one side is tighter, stretch it more. Fact: Only if the restriction is soft tissue. If it is joint structure, more stretching creates irritation. If it is motor control, stretching addresses the wrong system entirely.
Myth: A leg length difference needs a lift in the shoe. Fact: Differences under about 1cm are common and usually asymptomatic. Correction is generally considered for larger differences with symptoms, and that is a clinical decision.
Myth: Foam rolling the tight side will even things out. Fact: It produces a short-term change in stretch tolerance lasting minutes to hours. Useful as a warm-up, not a correction.
Myth: You can see asymmetry accurately in the mirror. Fact: You cannot. Standing posture varies minute to minute, and lighting plus your own visual bias make self-assessment unreliable. Measure range with a phone app or have someone film you.
FAQ: Asymmetry Questions, Answered
How much difference is normal?
Small differences in range and strength are found in nearly everyone. Differences above roughly 15 percent in strength, or clearly visible differences in range, are worth looking at.
Should I do extra sets on the weaker side?
A modest amount can help, but the bigger lever is leading each exercise with the weaker side and matching the stronger side to it rather than the reverse.
Why is my tight side sometimes the stronger one?
Commonly, yes. Tightness often reflects a muscle working harder or holding more tone, not one that is weak. This is why stretching a tight side sometimes makes it feel worse.
Can sleeping position cause asymmetry?
Six to eight hours a night in one position is a substantial exposure and plausibly contributes. Alternating sides is free and worth trying.
When should I see a professional?
Pain, worsening over months, sudden onset, any numbness or radiating symptoms, or a difference that limits a specific movement you need. Tightness alone, unchanging and painless, usually does not require it.
TL;DR:
- Asymmetry is normal - organ placement, handedness, small leg length differences, and habit positions all contribute.
- Separate the type: does it change with warm-up, what does end range feel like, and is passive range greater than active?
- A hard bony block will not respond to stretching. A control gap will not respond to stretching either.
- Lead every unilateral exercise with the restricted side and match the other side to it.
- Audit the eight hours of daily position before adding another ten minute routine.
If it is small, painless, and not limiting anything, the right answer is often to leave it alone.
Keep Reading
This article is for general informational purposes only and is not medical advice. Always consult a qualified health professional for guidance specific to you.
